Polio
Poliomyelitis, commonly shortened to polio, is an infectious disease caused by the poliovirus.[1] Approximately 75% of cases are asymptomatic;[5] mild symptoms which can occur include sore throat and fever; in a proportion of cases more severe symptoms develop such as headache, neck stiffness, and paresthesia.[1][3] These symptoms usually pass within one or two weeks.[1] A less common symptom is permanent paralysis, and possible death in extreme cases.[1] Years after recovery, post-polio syndrome may occur, with a slow development of muscle weakness similar to that which the person had during the initial infection.[2]
Polio occurs naturally only in humans.[1] It is highly infectious, and is spread from person to person either through fecal–oral transmission[1][6] (e.g. poor hygiene, or by ingestion of food or water contaminated by human feces), or via the oral–oral route.[1] Those who are infected may spread the disease for up to six weeks even if no symptoms are present.[1] The disease may be diagnosed by finding the virus in the feces or detecting antibodies against it in the blood.[1]
Poliomyelitis has existed for thousands of years, with depictions of the disease in ancient art.[1] The disease was first recognized as a distinct condition by the English physician Michael Underwood in 1789,[1][7] and the virus that causes it was first identified in 1909 by the Austrian immunologist Karl Landsteiner.[8][9] Major outbreaks started to occur in the late 19th century in Europe and the United States,[1] and in the 20th century, it became one of the most worrying childhood diseases.[10] Following the introduction of polio vaccines in the 1950s polio incidence declined rapidly.[1]
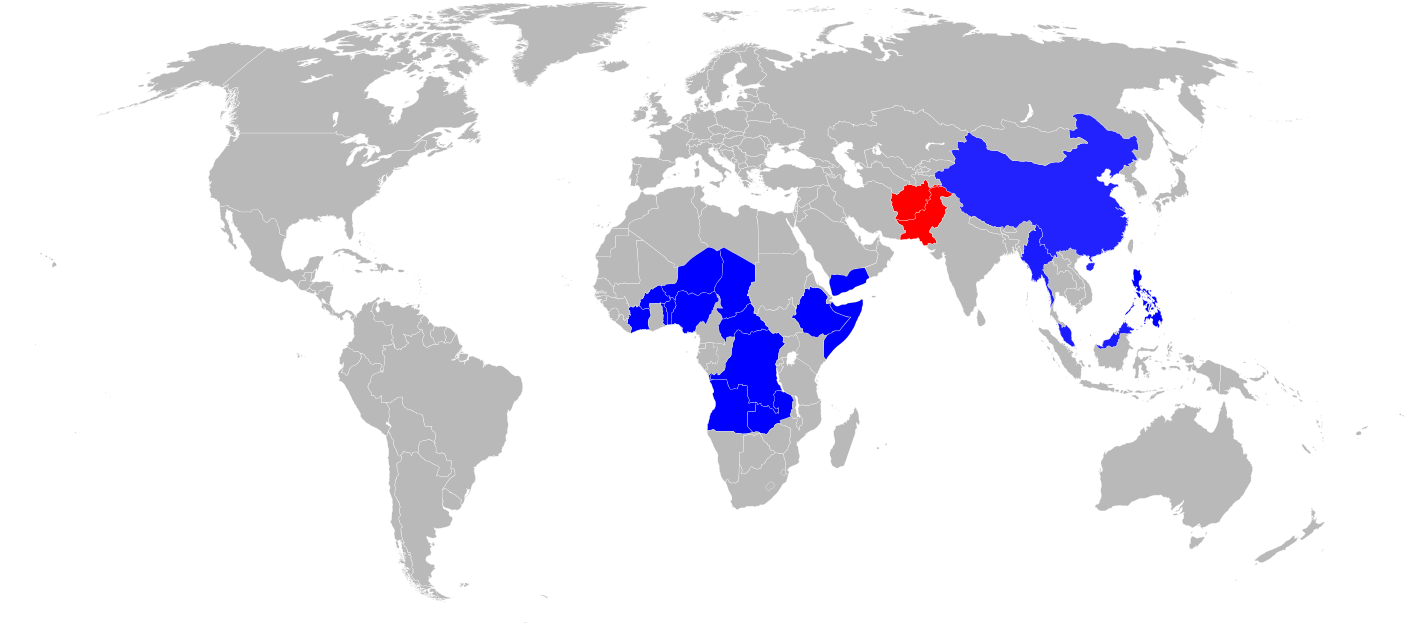
Once infected, there is no specific treatment.[3] The disease can be prevented by the polio vaccine, with multiple doses required for lifelong protection.[3] There are two broad types of polio vaccine; an injected vaccine using inactivated poliovirus and an oral vaccine containing attenuated (weakened) live virus.[1] Through the use of both types of vaccine, incidence of wild polio has decreased from an estimated 350,000 cases in 1988[3] to 30 confirmed cases in 2022, confined to just three countries.[11] There are rare incidents of disease transmission and/or of paralytic polio associated with the attenuated oral vaccine and for this reason the injected vaccine is preferred.[12]
Signs and symptoms
Outcomes of poliovirus infection in children| Outcome | Proportion of cases[1] |
| No symptoms | 72% |
|---|---|
| Minor illness | 24% |
Nonparalytic aseptic meningitis | 1–5% |
| Paralytic poliomyelitis | 0.1–0.5% |
| — Spinal polio | 79% of paralytic cases |
| — Bulbospinal polio | 19% of paralytic cases |
| — Bulbar polio | 2% of paralytic cases |
The term "poliomyelitis" is used to identify the disease caused by any of the three serotypes of poliovirus. Two basic patterns of polio infection are described: a minor illness which does not involve the central nervous system (CNS), sometimes called abortive poliomyelitis, and a major illness involving the CNS, which may be paralytic or nonparalytic.[13] Adults are more likely to develop symptoms, including severe symptoms, than children.[1]
In most people with a normal immune system, a poliovirus infection is asymptomatic. In about 25% of cases, the infection produces minor symptoms which may include sore throat and low fever.[3][5] These symptoms are temporary and full recovery occurs within one or two weeks.[1][3]
In about 1 percent of infections the virus can migrate from the gastrointestinal tract into the central nervous system (CNS).[1] Most patients with CNS involvement develop nonparalytic aseptic meningitis, with symptoms of headache, neck, back, abdominal and extremity pain, fever, vomiting, stomach pain, lethargy, and irritability.[14][15][16]
About one to five in 1000 cases progress to paralytic disease, in which the muscles become weak, floppy and poorly controlled, and, finally, completely paralyzed; this condition is known as acute flaccid paralysis.[17] The weakness most often involves the legs, but may less commonly involve the muscles of the head, neck, and diaphragm.[1] Depending on the site of paralysis, paralytic poliomyelitis is classified as spinal, bulbar, or bulbospinal. In those who develop paralysis, between 2 and 10 percent die as the paralysis affects the breathing muscles.[3]
Encephalitis, an infection of the brain tissue itself, can occur in rare cases, and is usually restricted to infants. It is characterized by confusion, changes in mental status, headaches, fever, and, less commonly, seizures and spastic paralysis.[18]
Cause
Main article: Poliovirus
 A TEM micrograph of poliovirus.
Poliomyelitis does not affect any species other than humans.[19] The disease is caused by infection with a member of the genus Enterovirus known as poliovirus (PV). This group of RNA viruses colonize the gastrointestinal tract[20] – specifically the oropharynx and the intestine. Its structure is quite simple, composed of a single (+) sense RNA genome enclosed in a protein shell called a capsid.[19]
In addition to protecting the virus' genetic material, the capsid proteins enable poliovirus to infect certain types of cells. Three serotypes of poliovirus have been identified – wild poliovirus type 1 (WPV1), type 2 (WPV2), and type 3 (WPV3) – each with a slightly different capsid protein.[21] All three are extremely virulent and produce the same disease symptoms.[19] PV1 is the most commonly encountered form, and the one most closely associated with paralysis.[22] WPV2 was certified as eradicated in 2015 and WPV3 certified as eradicated in 2019.[23]
The incubation period (from exposure to the first signs and symptoms) ranges from three to six days for nonparalytic polio. If the disease progresses to cause paralysis, this occurs within 7 to 21 days.[1]
Individuals who are exposed to the virus, either through infection or by immunization via polio vaccine, develop immunity. In immune individuals, IgA antibodies against poliovirus are present in the tonsils and gastrointestinal tract and able to block virus replication; IgG and IgM antibodies against PV can prevent the spread of the virus to motor neurons of the central nervous system.[24] Infection or vaccination with one serotype of poliovirus does not provide immunity against the other serotypes, and full immunity requires exposure to each serotype.[24]
A rare condition with a similar presentation, nonpoliovirus poliomyelitis, may result from infections with enteroviruses other than poliovirus.[25]
The oral polio vaccine contains weakened viruses that can replicate. On rare occasions, these may be transmitted from the vaccinated person to other people, who may display symptoms of polio. In communities with good vaccine coverage transmission is limited, and the virus dies out. In communities with low vaccine coverage, this weakened virus may continue to circulate.[26] Polio arising from this cause is referred to as circulating vaccine-derived polio (cVDPV) in order to distinguish it from the natural or "wild" poliovirus (WPV).[27]
Transmission
Poliomyelitis is highly contagious. The disease is transmitted primarily via the fecal–oral route, by ingesting contaminated food or water. It is occasionally transmitted via the oral–oral route.[1] It is seasonal in temperate climates, with peak transmission occurring in summer and autumn. These seasonal differences are far less pronounced in tropical areas.[24] Polio is most infectious between 7 and 10 days before and after the appearance of symptoms, but transmission is possible as long as the virus remains in the saliva or feces. Virus particles can be excreted in the feces for up to six weeks.[5]
Factors that increase the risk of polio infection include pregnancy,[28] the very old and the very young, immune deficiency,[29] and malnutrition.[30] Although the virus can cross the maternal-fetal barrier during pregnancy, the fetus does not appear to be affected by either maternal infection or polio vaccination.[31] Maternal antibodies also cross the placenta, providing passive immunity that protects the infant from polio infection during the first few months of life.[32]
Pathophysiology
 A photomicrograph of the lumbar spinal cord depicting an infarct due to Polio Type III surrounding the anterior spinal artery.
Poliovirus enters the body through the mouth, infecting the first cells with which it comes in contact – the pharynx and intestinal mucosa. It gains entry by binding to an immunoglobulin-like receptor, known as the poliovirus receptor or CD155, on the cell membrane.[33]
The virus then hijacks the host cell's own machinery, and begins to replicate. Poliovirus divides within gastrointestinal cells for about a week, from where it spreads to the tonsils (specifically the follicular dendritic cells residing within the tonsilar germinal centers), the intestinal lymphoid tissue including the M cells of Peyer's patches, and the deep cervical and mesenteric lymph nodes, where it multiplies abundantly. The virus is subsequently absorbed into the bloodstream.[34]
Known as viremia, the presence of a virus in the bloodstream enables it to be widely distributed throughout the body. Poliovirus can survive and multiply within the blood and lymphatics for long periods of time, sometimes as long as 17 weeks.[35] In a small percentage of cases, it can spread and replicate in other sites, such as brown fat, the reticuloendothelial tissues, and muscle.[36]
This sustained replication causes a major viremia, and leads to the development of minor influenza-like symptoms. Rarely, this may progress and the virus may invade the central nervous system, provoking a local inflammatory response. In most cases, this causes a self-limiting inflammation of the meninges, the layers of tissue surrounding the brain, which is known as nonparalytic aseptic meningitis.[14] Penetration of the CNS provides no known benefit to the virus, and is quite possibly an incidental deviation of a normal gastrointestinal infection.[37] The mechanisms by which poliovirus spreads to the CNS are poorly understood, but it appears to be primarily a chance event – largely independent of the age, gender, or socioeconomic position of the individual.[37]
Paralytic polio
 Denervation of skeletal muscle tissue secondary to poliovirus infection can lead to paralysis.
In around one percent of infections, poliovirus spreads along certain nerve fiber pathways, preferentially replicating in and destroying motor neurons within the spinal cord, brain stem, or motor cortex. This leads to the development of paralytic poliomyelitis, the various forms of which (spinal, bulbar, and bulbospinal) vary only with the amount of neuronal damage and inflammation that occurs, and the region of the CNS affected.
The destruction of neuronal cells produces lesions within the spinal ganglia; these may also occur in the reticular formation, vestibular nuclei, cerebellar vermis, and deep cerebellar nuclei.[37] Inflammation associated with nerve cell destruction often alters the color and appearance of the gray matter in the spinal column, causing it to appear reddish and swollen.[14] Other destructive changes associated with paralytic disease occur in the forebrain region, specifically the hypothalamus and thalamus.[37] The molecular mechanisms by which poliovirus causes paralytic disease are poorly understood.
Early symptoms of paralytic polio include high fever, headache, stiffness in the back and neck, asymmetrical weakness of various muscles, sensitivity to touch, difficulty swallowing, muscle pain, loss of superficial and deep reflexes, paresthesia (pins and needles), irritability, constipation, or difficulty urinating. Paralysis generally develops one to ten days after early symptoms begin, progresses for two to three days, and is usually complete by the time the fever breaks.[38]
The likelihood of developing paralytic polio increases with age, as does the extent of paralysis. In children, nonparalytic meningitis is the most likely consequence of CNS involvement, and paralysis occurs in only one in 1000 cases. In adults, paralysis occurs in one in 75 cases.[39] In children under five years of age, paralysis of one leg is most common; in adults, extensive paralysis of the chest and abdomen also affecting all four limbs – quadriplegia – is more likely.[40] Paralysis rates also vary depending on the serotype of the infecting poliovirus; the highest rates of paralysis (one in 200) are associated with poliovirus type 1, the lowest rates (one in 2,000) are associated with type 2.[41]
Spinal polio
Spinal polio, the most common form of paralytic poliomyelitis, results from viral invasion of the motor neurons of the anterior horn cells, or the ventral (front) grey matter section in the spinal column, which are responsible for movement of the muscles, including those of the trunk, limbs, and the intercostal muscles.[17] Virus invasion causes inflammation of the nerve cells, leading to damage or destruction of motor neuron ganglia. When spinal neurons die, Wallerian degeneration takes place, leading to weakness of those muscles formerly innervated by the now-dead neurons.[42]
With the destruction of nerve cells, the muscles no longer receive signals from the brain or spinal cord; without nerve stimulation, the muscles atrophy, becoming weak, floppy and poorly controlled, and finally completely paralyzed.[17] Maximum paralysis progresses rapidly (two to four days), and usually involves fever and muscle pain. Deep tendon reflexes are also affected, and are typically absent or diminished; sensation (the ability to feel) in the paralyzed limbs, however, is not affected.[43]
The extent of spinal paralysis depends on the region of the cord affected, which may be cervical, thoracic, or lumbar.[44] The virus may affect muscles on both sides of the body, but more often the paralysis is asymmetrical.[34] Any limb or combination of limbs may be affected – one leg, one arm, or both legs and both arms. Paralysis is often more severe proximally (where the limb joins the body) than distally (the fingertips and toes).[34]
Bulbar polio
...
Prevention
Passive immunization
In 1950, William Hammon at the University of Pittsburgh purified the gamma globulin component of the blood plasma of polio survivors.[47] Hammon proposed the gamma globulin, which contained antibodies to poliovirus, could be used to halt poliovirus infection, prevent disease, and reduce the severity of disease in other patients who had contracted polio. The results of a large clinical trial were promising; the gamma globulin was shown to be about 80 percent effective in preventing the development of paralytic poliomyelitis.[48] It was also shown to reduce the severity of the disease in patients who developed polio.[47] Due to the limited supply of blood plasma gamma globulin was later deemed impractical for widespread use and the medical community focused on the development of a polio vaccine.[49]
Vaccine
Main article: Polio vaccine

A child receiving an oral polio vaccine.
Two types of vaccine are used throughout the world to combat polio. Both types induce immunity to polio and are effective in protecting individuals from disease.
The first candidate polio vaccine, based on one serotype of a live but attenuated (weakened) virus, was developed by the virologist Hilary Koprowski. Koprowski's prototype vaccine was given to an eight-year-old boy on 27 February 1950.[50] Koprowski continued to work on the vaccine throughout the 1950s, leading to large-scale trials in the then Belgian Congo and the vaccination of seven million children in Poland against serotypes PV1 and PV3 between 1958 and 1960.[51]
The second polio virus vaccine was developed in 1952 by Jonas Salk at the University of Pittsburgh, and announced to the world on 12 April 1955.[52][53] The Salk vaccine, or inactivated poliovirus vaccine (IPV), is based on poliovirus grown in a type of monkey kidney tissue culture (vero cell line), which is chemically inactivated with formalin.[24] After two doses of inactivated poliovirus vaccine (given by injection), 90 percent or more of individuals develop protective antibody to all three serotypes of poliovirus, and at least 99 percent are immune to poliovirus following three doses.[1]
Subsequently, Albert Sabin developed another live, oral polio vaccine (OPV). It was produced by the repeated passage of the virus through nonhuman cells at subphysiological temperatures.[54] The attenuated poliovirus in the Sabin vaccine replicates very efficiently in the gut, the primary site of wild poliovirus infection and replication, but the vaccine strain is unable to replicate efficiently within nervous system tissue.[55]
A single dose of Sabin's oral polio vaccine produces immunity to all three poliovirus serotypes in about 50 percent of recipients. Three doses of live-attenuated oral vaccine produce protective antibody to all three poliovirus types in more than 95 percent of recipients.[1] Human trials of Sabin's vaccine began in 1957,[56] and in 1958, it was selected, in competition with the live vaccines of Koprowski and other researchers, by the US National Institutes of Health.[51] Licensed in 1962,[56] it rapidly became the only polio vaccine used worldwide.[51]
OPV efficiently blocks person-to-person transmission of wild poliovirus by oral–oral and fecal–oral routes, thereby protecting both individual vaccine recipients and the wider community (herd immunity).[57] IPV confers good immunity but is less effective at preventing spread of wild poliovirus by the fecal–oral route.[58]
 Wild polio vs cVDVP cases (2000–2019).
Because the oral polio vaccine is inexpensive, easy to administer, and produces excellent immunity in the intestine (which helps prevent infection with wild virus in areas where it is endemic), it has been the vaccine of choice for controlling poliomyelitis in many countries.[59] On very rare occasions (about one case per 750,000 vaccine recipients), the attenuated virus in the oral polio vaccine reverts into a form that can paralyze.[60] In 2017, cases caused by vaccine-derived poliovirus (cVDPV) outnumbered wild poliovirus cases for the first time, due to wild polio cases hitting record lows.[61] Most industrialized countries have switched to inactivated polio vaccine, which cannot revert, either as the sole vaccine against poliomyelitis or in combination with oral polio vaccine.[62]
Treatment
There is no cure for polio, but there are treatments. The focus of modern treatment has been on providing relief of symptoms, speeding recovery and preventing complications. Supportive measures include antibiotics to prevent infections in weakened muscles, analgesics for pain, moderate exercise and a nutritious diet.[63] Treatment of polio often requires long-term rehabilitation, including occupational therapy, physical therapy, braces, corrective shoes and, in some cases, orthopedic surgery.[44]
Portable ventilators may be required to support breathing. Historically, a noninvasive, negative-pressure ventilator, more commonly called an iron lung, was used to artificially maintain respiration during an acute polio infection until a person could breathe independently (generally about one to two weeks). Today, many polio survivors with permanent respiratory paralysis use modern jacket-type negative-pressure ventilators worn over the chest and abdomen.[64]
Other historical treatments for polio include hydrotherapy, electrotherapy, massage and passive motion exercises, and surgical treatments, such as tendon lengthening and nerve grafting.[17]
Sister Elizabeth Kenny's Kenny regimen is now the hallmark for the treatment of paralytic polio.[65]
Prognosis
...
History
See also: History of poliomyelitis and List of poliomyelitis survivors
 An Egyptian stele thought to represent a person with polio, 18th Dynasty (1403–1365 BC).
The effects of polio have been known since prehistory; Egyptian paintings and carvings depict otherwise healthy people with withered limbs, and young children walking with canes.[148] The earliest known case of polio is indicated by the remains of a teenage girl discovered in a 4000-year-old burial site in the United Arab Emirates, exhibiting characteristic symptoms of the condition.[149]
The first clinical description was provided by the English physician Michael Underwood in 1789, where he refers to polio as "a debility of the lower extremities".[150] The work of physicians Jakob Heine in 1840 and Karl Oskar Medin in 1890 led to it being known as Heine–Medin disease.[151] The disease was later called infantile paralysis, based on its propensity to affect children.
Before the 20th century, polio infections were rarely seen in infants before six months of age, most cases occurring in children six months to four years of age. Poorer sanitation of the time resulted in constant exposure to the virus, which enhanced a natural immunity within the population. In developed countries during the late 19th and early 20th centuries, improvements were made in community sanitation, including better sewage disposal and clean water supplies. These changes drastically increased the proportion of children and adults at risk of paralytic polio infection, by reducing childhood exposure and immunity to the disease.[152]
Small localized paralytic polio epidemics began to appear in Europe and the United States around 1900.[153] Outbreaks reached pandemic proportions in Europe, North America, Australia, and New Zealand during the first half of the 20th century. By 1950, the peak age incidence of paralytic poliomyelitis in the United States had shifted from infants to children aged five to nine years, when the risk of paralysis is greater; about one-third of the cases were reported in persons over 15 years of age.[154]
Accordingly, the rate of paralysis and death due to polio infection also increased during this time.[153] In the United States, the 1952 polio epidemic became the worst outbreak in the nation's history. Of the nearly 58,000 cases reported that year, 3,145 died and 21,269 were left with mild to disabling paralysis.[155] Intensive care medicine has its origin in the fight against polio.[156] Most hospitals in the 1950s had limited access to iron lungs for patients unable to breathe without mechanical assistance. Respiratory centers designed to assist the most severe polio patients, first established in 1952 at the Blegdam Hospital of Copenhagen by Danish anesthesiologist Bjørn Ibsen, were the precursors of modern intensive care units (ICU). (A year later, Ibsen would establish the world's first dedicated ICU.)[157]
The polio epidemics not only altered the lives of those who survived them, but also brought profound cultural changes, spurring grassroots fund-raising campaigns that would revolutionize medical philanthropy, and giving rise to the modern field of rehabilitation therapy. As one of the largest disabled groups in the world, polio survivors also helped to advance the modern disability rights movement through campaigns for the social and civil rights of the disabled.
The World Health Organization estimates that there are 10 to 20 million polio survivors worldwide.[158] In 1977, there were 254,000 persons living in the United States who had been paralyzed by polio.[159] According to doctors and local polio support groups, some 40,000 polio survivors with varying degrees of paralysis were living in Germany, 30,000 in Japan, 24,000 in France, 16,000 in Australia, 12,000 in Canada and 12,000 in the United Kingdom in 2001.[158] Many notable individuals have survived polio and often credit the prolonged immobility and residual paralysis associated with polio as a driving force in their lives and careers.[160]
The disease was very well publicized during the polio epidemics of the 1950s, with extensive media coverage of any scientific advancements that might lead to a cure. Thus, the scientists working on polio became some of the most famous of the century. Fifteen scientists and two laymen who made important contributions to the knowledge and treatment of poliomyelitis are honored by the Polio Hall of Fame, which was dedicated in 1957 at the Roosevelt Warm Springs Institute for Rehabilitation in Warm Springs, Georgia, US. In 2008 four organizations (Rotary International, the World Health Organization, the U.S. Centers for Disease Control and UNICEF) were added to the Hall of Fame.[161][162]
World Polio Day (24 October) was established by Rotary International to commemorate the birth of Jonas Salk, who led the first team to develop a vaccine against poliomyelitis. Use of this inactivated poliovirus vaccine and subsequent widespread use of the oral poliovirus vaccine developed by Albert Sabin led to establishment of the Global Polio Eradication Initiative (GPEI) in 1988. Since then, GPEI has reduced polio worldwide by 99 percent.[163]
Etymology
The term derives from the Ancient Greek poliós (πολιός), meaning "grey", myelós (µυελός "marrow"), referring to the grey matter of the spinal cord, and the suffix -itis, which denotes inflammation,[14] i.e., inflammation of the spinal cord's grey matter, although a severe infection can extend into the brainstem and even higher structures, resulting in polio*encephal*itis, resulting in inability to breathe, requiring mechanical assistance such as an iron lung...